

 Fluoxetine for Anxiety: Evidence and Use Cases — Panic, Ocd, Gad Dosing and Outcomes
How This Ssri Works: Brain Chemistry and Relief
Imagine the knot in your chest loosening as signals in the brain find a softer rhythm; fluoxetine increases synaptic serotonin by blocking reuptake, gently recalibrating amygdala-prefrontal connectivity and lowering reactive fear circuits over time
At a cellular level neurons recieve signals differently; enhanced serotonin tone modulates receptor cascades, shifts plasticity, and reduces exaggerated threat appraisal. Patients often report subtle calm within weeks, with fuller benefit emerging after sustained treatment
Clinical relief is not uniform: anxiety types respond variably, with panic and OCD often needing higher doses or longer trials than generalized anxiety. Combining therapy with medication improves learning of new coping habits and resilience
Monitoring focuses on side effects, drug interactions, and patient experience; clinicians track mood, sleep, and emergent agitation early in treatment.
| Mechanism | Effect |
|---|---|
| Reuptake inhibition | Increased synaptic serotonin, circuit modulation |
| Timecourse | Weeks to months for full response |
Evidence from Trials for Panic, Ocd, Gad
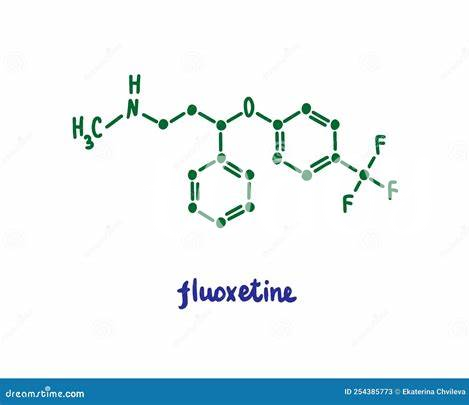
Large randomized trials and meta-analyses show fluoxetine reduces core symptoms in panic disorder, obsessive–compulsive disorder and generalized anxiety disorder, with effect sizes modest to moderate. In panic, attack frequency and anticipatory anxiety decline; in OCD, obsessions and compulsions fall, often with CBT or as monotherapy; in GAD, trials report improvement in worry and somatic tension. Placebo-controlled data show early symptom dampening though remission rates vary.
Clinicians should note variable response timelines and relapse risk after discontinuation; acute response may begin within two to four weeks, but optimal benefit often needs eight to twelve weeks. Adverse events and study dropouts are documented, so shared decision-making and monitoring for side effects is key. Trial populations are heterogenous, so individual outcomes may differ and clinicians must Recieve and interpret trial data in context, using CBT integration when appropriate; occassionally combination therapy improves outcomes
Dosing Strategies: Starting Doses, Titration, Target Ranges
At the clinic, a young patient asked about fluoxetine and relief; we began conservatively, choosing modest initial amounts to watch tolerance. The Begining approach reduced early adverse effects and built trust between clinician and patient.
We increase doses gradually, usually by small increments each week, tailoring choices to diagnosis: panic, OCD, GAD. Goal is often a mid-range dose; some patients need higher maintenance; monitor response and side effects closely Occassionally.
Typical therapeutic windows span roughly twenty to sixty milligrams depending on severity and diagnosis; clinicians aim for meaningful symptom control without undue side effects. Rarely higher doses are trialed under close supervision with interaction checks.
Long-term plans prioritize adherence, periodic review, and gradual discontinuation when appropriate; fluoxetine’s long half-life makes abrupt withdrawal less problematic than some SSRIs, but planned reductions over weeks reduce relapse risk and address patient concerns effectively.
Timeline of Effect: Onset, Response, and Remission Rates

A patient often describes the first days on fluoxetine with sleep or appetite shifts, Occassionally a transient increase in anxiety. Clinicians should prepare patients for this possibility, which can be managed with ongoing watchful follow-up.
Early symptomatic change can be subtle: some notice reduced panic frequency or clearer thinking within 1–2 weeks, and sometimes anxiety relief more reliably appears around 4–6 weeks after starting. Full response typically requires 8–12 weeks.
Remission rates vary. For GAD and panic disorder many trials report 40–60% achieving response or remission; OCD often shows lower remission without higher doses and longer trials. Individual factors and adherence strongly influence outcomes overall.
Clinically, patience is rewarded: continue fluoxetine for at least 8–12 weeks at a therapeutic dose before judging efficacy. If partial response occurs, consider optimization or augmentation; maintain treatment months after remission to reduce relapse risk.
Side Effects, Interactions, and Monitoring Best Practices
Patients starting fluoxetine often report jitteriness, sleep changes, gastrointestinal upset, or sexual dysfunction. Teh first weeks can be rough; symptoms usually attenuate but serotonin syndrome risk rises with MAOI or triptan combos, so review meds.
Monitoring includes baseline weight, blood pressure, and periodic review of suicidal ideation in younger patients. Labs are rarely required; consider pregnancy test and electrolytes if diuretics used.
| Test | Indication |
|---|---|
| Pregnancy | Before conception or if indicated |
| Electrolytes | If on diuretics |
Discuss adherence strategies: simplify dosing, counsel about sexual side effects, and delay dose changes until steady state. Warn about alcohol and stimulants. If partial response at 8-12 weeks, consider dose escalation or augmentation with buspirone or psychotherapy to acheive remission. Schedule follow-up to monitor tolerability regularly.
Clinical Vignettes: Outcomes, Adherence, and Troubleshooting
A young patient began fluoxetine 10 mg, increased to 20 mg; panic attacks decreased and functioning improved within six weeks.
An adult with OCD combined SSRIs with CBT and reached response on 40 mg after three months; side effects were occassionally nausea.
GAD patients may need longer exposure; some respond to 20 mg while others require 40–60 mg. Adherence support and education boost outcomes.
When insomnia or activation appears, dose timing or slower titration helps; check interactions and consider switching if no improvement by three months. Consult clinician NCBI DailyMed