

 Comparing Nsaids: Diclofenac Vs Ibuprofen — Pros and Cons
How They Work: Cox Inhibition and Pain Pathways
Imagine inflammation as a blaring alarm: damaged tissue releases prostaglandins that sensitize nociceptors and amplify pain signals. NSAIDs reduce that alarm by blocking cyclooxygenase enzymes (COX-1 and COX-2), cutting prostaglandin production. Ibuprofen is a broadly nonselective inhibitor, while diclofenac leans toward COX-2, which can yield stronger anti-inflammatory effects at similar doses.
Beyond the periphery, lowering prostaglandin levels in the spinal cord and brain reduces central sensitisation and fever, explaining systemic relief. The balance between COX-1 and COX-2 inhibition shapes efficacy and side effects: COX-2 preference often improves anti-inflammatory potency but may spare less gastric protection. Clinicians weigh these pharmacodynamic differences when matching an NSAID’s mechanism to a patient’s pain profile. Individual response also varies widely.
| Drug | COX preference | Main effect |
|---|---|---|
| Ibuprofen | Nonselective | Analgesic/anti-inflammatory |
| Diclofenac | COX-2–leaning | Potent anti-inflammatory |
Speed and Duration: Who Relieves Pain Faster

Many patients report faster relief with diclofenac, which can act quickly after oral or topical application and sometimes feels more potent than ibuprofen. Both drugs inhibit prostaglandin synthesis, but differences in absorption and formulation mean onset and peak effect vary between preparations and individuals.
Choose a formulation to match needs: immediate-release for acute flare-ups, extended-release for sustained control, or topical for localized pain with lower systemic exposure. Consider dosing intervals, underlying conditions and drug interactions; clinicians balance faster onset against duration, safety profile and individual patient preference when recommending therapy.
Safety Profile: Gastrointestinal and Cardiovascular Risk Trade-offs
Clinicians weigh benefits against harms when choosing an NSAID, picturing stomach ulcers on one side and heart risks on the other. Patient history and concurrent medications tilt that balance.
Diclofenac can offer potent pain relief but carries a somewhat higher cardiovascular signal than some alternatives, while traditional GI injury remains a shared concern requiring preventive strategies like PPIs.
Risk rises with dose and duration; low doses and shortest effective courses reduce harm. Co-prescription of gastroprotective agents, screening, and monitoring improve safety for vulnerable patients including older adults.
Shared decision making matters: discuss personal cardiovascular and GI history, concomitant drugs like anticoagulants, and preferred analgesic trade-offs before selecting diclofenac or ibuprofen to minimize avoidable adverse events.
Dosing, Forms, and Practical Administration Tips
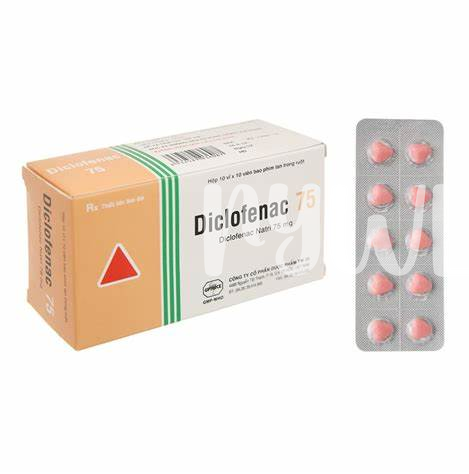
Choose oral tablets or topical gels based on pain location and systemic needs. Oral diclofenac is commonly available as 50 mg or 75 mg; follow prescribed intervals and never exceed the daily limit. Short courses for flares minimize risk.
Topical forms like gels, patches, or drops concentrate effect at the target and usually cause fewer systemic effects. Apply as directed, avoid open wounds, and wash hands after use to prevent eye contact.
Take pills with food to reduce stomach upset and space doses evenly. Check interactions before combining therapies regularly.
Special Populations: Pregnancy, Elderly, Children Considerations
In pregnancy NSAID use is cautious; after 30 weeks they risk fetal ductus closure. Diclofenac should usually be avoided and only considered with obstetric advice assessing maternal versus fetal risk.
Older adults face higher GI, renal, and bleeding risks; start low and monitor blood pressure and creatinine. Short courses at the lowest effective dose reduce harm, and avoid diclofenac exposure.
In children, ibuprofen is the usual choice with established pediatric dosing; diclofenac is less common. Use age-appropriate formulations, calculate dose by weight, and seek pediatric advice for prolonged therapy safely.
| Population | Key point |
|---|---|
| Pregnancy | Avoid after 30 weeks; consult obstetrician |
| Older adults | Start low; monitor renal, BP, GI risks |
| Children | Use pediatric dosing; weight-based calculations |
Choosing Wisely: Clinical Scenarios and Prescribing Guidance
When deciding between diclofenac and ibuprofen, think about the clinical context: short-term muscle strain or fever favors ibuprofen for safety and availability, while localized inflammatory conditions (like ankylosing spondylitis) may benefit from diclofenac's potency. Consider prior response, comorbidities, and concurrent medications.
For patients with cardiovascular risk, minimize diclofenac use and prefer the lowest effective dose for the shortest duration; ibuprofen also carries risk but is generally less concerning than diclofenac for cardiac outcomes. For GI-sensitive individuals, co-prescribe a PPI or select alternative analgesics.
In acute care choose fast-acting formulations (oral solution or gel for diclofenac at the site), and document indication, duration, and review need at follow-up. Shared decision-making ensures risks align with patient priorities. When chronic therapy is contemplated, involve specialists (rheumatology or cardiology) to tailor long-term strategies, and regularly monitor renal, hepatic function, blood pressure, and medication adherence.